

For millions of people living with major depressive disorder, psychiatric medicine can feel like an exhausting game of trial and error. Standard clinical protocol dictates cycling through selective serotonin reuptake inhibitors (SSRIs), serotonin-norepinephrine reuptake inhibitors (SNRIs), and atypical antidepressants. Each attempt requires six to eight weeks of waiting, often accompanied by frustrating side effects like weight gain, fatigue, and emotional blunting, only to result in minimal symptom relief. When two or more adequate medication trials fail to produce meaningful clinical improvement, the condition is classified as treatment-resistant depression (TRD).
In recent years, ketamine has emerged from the fringes of operating rooms and underground culture to become one of the most significant developments in modern interventional psychiatry. Media coverage has swung wildly between heralding it as an instant miracle cure and cautioning against its history as a dissociative anesthetic. The clinical reality sits between those two extremes. Ketamine is neither a permanent panacea nor an unregulated hazard; it is a rapid-acting, biologically distinct intervention that can disrupt entrenched depressive episodes when administered within an appropriate clinical framework.
How Ketamine Diverges from Conventional Antidepressants
To understand why ketamine succeeds where traditional medications often fail, one must examine the neurochemistry of the depressed brain. For decades, psychiatric treatment was guided primarily by the monoamine hypothesis, which posited that depression stemmed from a simple deficit in neurotransmitters like serotonin, norepinephrine, or dopamine. While standard medications slowly increase the concentration of these chemicals in the synaptic cleft, they do little to immediately repair the physical architecture of the brain.
Chronic stress and prolonged depression cause atrophy in key brain regions, particularly the prefrontal cortex and the hippocampus. Over time, dendritic spines—the microscopic connections neurons use to communicate—shrink and disconnect, leaving the brain in a state of rigid, inflexible despair.
Ketamine operates through an entirely different biological pathway by targeting the glutamate system, the brain’s primary excitatory neurotransmitter. Specifically, ketamine acts as an N-methyl-D-aspartate (NMDA) receptor antagonist. By temporarily blocking these receptors, it triggers an immediate surge of glutamate, activating secondary AMPA receptors.
This biochemical cascade stimulates the release of brain-derived neurotrophic factor (BDNF), a critical protein that acts as fertilizer for brain cells. Within hours of administration, ketamine prompts synaptogenesis—the physical regrowth of damaged synaptic connections. Rather than merely adjusting emotional volume, it temporarily restores neuroplasticity, allowing the brain to break free from repetitive, negative cognitive loops.
Clinical Administration: IV Infusions vs. Intranasal Esketamine
Ketamine therapy is not a single, uniform procedure. In clinical practice, patients generally encounter two primary therapeutic formats, each with distinct practical and financial realities.
Intravenous (IV) Ketamine Infusions
Administered primarily in specialized outpatient clinics, IV infusion represents the original clinical model for psychiatric ketamine. A low, sub-anesthetic dose (typically around 0.5 milligrams per kilogram of body weight) is delivered slowly over forty to fifty minutes.
-
Bioavailability and Control: Because the medication enters the bloodstream directly, IV delivery provides 100% bioavailability. If a patient experiences acute distress or adverse physiological reactions, the infusion pump can be slowed or halted immediately, clearing the drug from circulation within minutes.
-
Off-Label Status: While generic ketamine has been approved by the FDA as an anesthetic for decades, its use for psychiatric conditions remains off-label. Consequently, commercial health insurance rarely covers the cost of IV infusions, leaving patients to pay out-of-pocket fees that typically range from $400 to $800 per session.
Intranasal Esketamine (Spravato)
In 2019, the FDA approved esketamine, the S-enantiomer molecule of ketamine, specifically for treatment-resistant depression in adults. Formulated as a nasal spray, it must be taken alongside an oral antidepressant.
-
Structured Safety Protocols: Esketamine is strictly regulated under a Risk Evaluation and Mitigation Strategy (REMS) program. Patients must self-administer the spray inside a certified medical facility under the direct supervision of a healthcare provider. They are required to remain in the clinic for at least two hours of blood pressure and psychological monitoring before being discharged to an adult driver.
-
Insurance Coverage: Because it holds formal FDA approval, esketamine is far more likely to be covered by private insurance and Medicare, though securing coverage often requires extensive documentation proving prior medication failures.
What to Expect During a Treatment Session
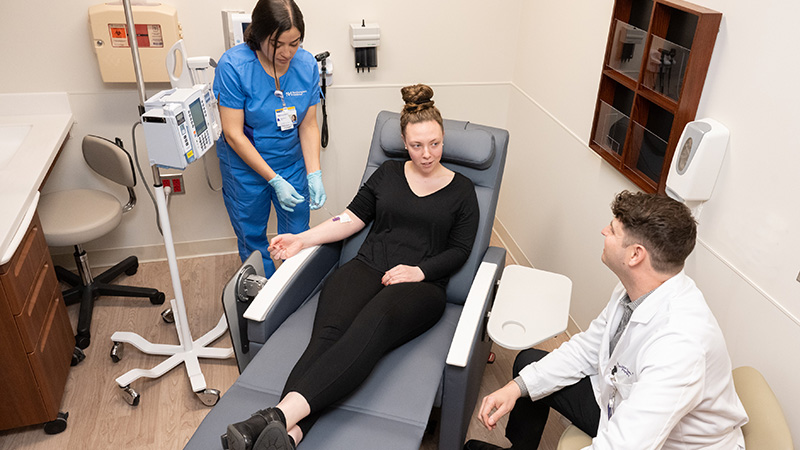
Walking into a ketamine clinic is distinctly different from visiting a conventional therapist or psychiatrist. The setting is intentionally designed to minimize external sensory input, featuring dim lighting, comfortable reclining chairs, noise-canceling headphones playing ambient music, and eye masks.
Within ten to fifteen minutes of administration, patients typically experience mild to moderate dissociation. This state often involves a feeling of detachment from one’s physical body, an altered perception of time, and a softening of the internal narrative voice. Visual distortions, floating sensations, and dream-like emotional processing are common. For many individuals, this temporary detachment offers relief by providing an objective, calm vantage point from which to view past trauma or chronic depressive thoughts without the accompanying emotional pain.
Clinically, the primary side effects are transient. Blood pressure and heart rate temporarily elevate during the active phase, which is why clinics monitor vitals before, during, and after the session. Light nausea, mild dizziness, and grogginess can occur, though anti-nausea medications like ondansetron are frequently administered beforehand to maintain physical comfort. Within an hour of completing the infusion or nasal dose, the psychoactive effects dissipate, leaving the patient fully lucid, though often mentally fatigued.
Durability, Maintenance, and Real-World Limitations
The most persistent misconception surrounding ketamine therapy is that a single session or short series acts as a permanent cure. Ketamine is an acute intervention designed to rebuild neural capacity; it does not permanently insulate the brain from life stressors or biological vulnerabilities.
Standard treatment protocols begin with an induction phase, usually consisting of six sessions spaced over two to three weeks. If a patient responds favorably—often evidenced by a lifting of brain fog, improved emotional range, or a sharp decline in suicidal ideation within twenty-four to seventy-two hours—the schedule shifts into a maintenance phase.
Maintenance intervals vary widely between individuals. Some patients maintain their clinical gains with a single booster session every few months, while others find their depressive symptoms resurfacing within two to three weeks without ongoing treatment. Furthermore, ketamine is not appropriate for everyone. Individuals with a personal history of psychosis, active mania, uncontrolled cardiovascular disease, or unstable substance use disorders are typically disqualified from treatment due to clinical safety risks.
The Critical Role of Integration and Psychotherapy
The true therapeutic value of ketamine lies not merely in the temporary psychedelic or dissociative experience, but in the neuroplastic window that opens in the days immediately following a session.
For forty-eight to seventy-two hours post-treatment, the brain demonstrates elevated synaptic flexibility. Destructive cognitive grooves are softened, making the mind uniquely receptive to forming new perspectives, emotional habits, and behavioral routines. If a patient returns immediately to an unhealthy environment, chronic isolation, and negative self-talk, that biological opportunity is largely wasted.
To achieve lasting recovery, ketamine is increasingly paired with specialized psychotherapy, often referred to as Ketamine-Assisted Psychotherapy (KAP). Working with a mental health professional during the neuroplastic window allows individuals to process insights gained during the treatment, dismantle ingrained cognitive distortions, and practice adaptive coping strategies. Engaging in daily physical movement, prioritizing restorative sleep, and reinforcing positive social connections during this recovery window helps cement the newly formed neural pathways.
Ketamine therapy represents a profound shift in psychiatric medicine, offering rapid relief to individuals who have spent years navigating treatment-resistant despair. Approaching the treatment with realistic expectations, professional supervision, and a dedicated commitment to long-term psychological integration ensures that this medical tool can deliver on its genuine potential to restore vitality and mental clarity.
